What Is Retinal Detachment and Why Does It Need Prompt Medical Attention?
The visual system depends on the precise anatomical alignment and metabolic support of the neurosensory retina, the specialized light-sensitive neural tissue lining the posterior inner surface of the eye. Functionally, the retina converts incoming light stimuli into electrical impulses, which are transmitted via the optic nerve to the visual cortex. Histologically, the retina consists of ten distinct layers, broadly divided into two main functional components: the inner neurosensory retina (containing photoreceptor cells, bipolar neurons, and ganglion cells) and the outer retinal pigment epithelium (RPE). Under physiological conditions, the retinal pigment epithelium provides vital metabolic support, phagocytoses photoreceptor outer segments, maintains fluid balance, and continuously adheres to the neurosensory layer through active ion transport and biochemical adhesion. Retinal detachment occurs when the neurosensory retina physically separates from the underlying retinal pigment epithelium, disrupting metabolic exchange and setting off a cascade of rapid photoreceptor degradation and permanent visual loss if not managed promptly.
Pathophysiology and Mechanisms of Retinal Separation
Retinal detachment is classified into three primary mechanistic categories: rhegmatogenous, tractional, and exudative (serous) detachment. Rhegmatogenous retinal detachment represents the most prevalent form and arises from a full-thickness defect or tear in the neurosensory retina. As the eye ages, the gel-like vitreous humor undergoes liquefaction (synchysis) and detaches from the inner retinal surface, a process known as posterior vitreous detachment (PVD). If the vitreous body remains abnormally adherent to peripheral retinal sites, dynamic movement of the eye exerts localized vitreoretinal traction, pulling on the tissue and creating a retinal tear or hole. Once a break forms, liquefied vitreous fluid enters the subretinal space through the tear, driven by intraocular pressure differentials and ocular movements. As fluid accumulates, it progressively peels the neurosensory retina away from the underlying pigment epithelium, expanding the zone of detachment.
Tractional and Exudative Detachment Mechanisms
Tractional retinal detachment occurs without an initial full-thickness retinal tear. Instead, it develops when fibrovascular membranes contract along the inner surface of the retina, exerting mechanical force that pulls the neurosensory layer away from the retinal pigment epithelium. This mechanism is frequently seen in advanced proliferative diabetic retinopathy, retinal vein occlusions, and retinopathy of prematurity, where chronic ischemia stimulates pathological neovascularization and fibrous tissue proliferation. Exudative or serous retinal detachment occurs when fluid accumulates within the subretinal space in the absence of a retinal tear or physical traction. This form results from breakdown of the blood-retinal barrier, driven by severe inflammatory conditions (such as posterior uveitis or Vogt-Koyanagi-Harada disease), choroidal tumors (like choroidal melanoma), or systemic hypertensive disorders, allowing fluid to exude directly into the subretinal space.
Clinical Manifestations and Warning Symptoms
The development of a rhegmatogenous retinal detachment is typically preceded by characteristic warning symptoms that reflect acute vitreoretinal mechanical changes. As posterior vitreous traction pulls on the retina, physical stimulation of photoreceptors triggers photopsia—sudden, brief flashes of light, most noticeable in dim environments or during rapid eye movements. Simultaneously, as the vitreous separates or a retinal tear disrupts tiny retinal capillaries, microscopic cellular debris or red blood cells enter the vitreous cavity, casting dynamic shadows on the retina perceived by the patient as a sudden shower of new floaters, cobwebs, or dark spots. As the neurosensory layer begins to detach, patients observe a dark, shadow-like curtain or veil advancing across their peripheral field of vision. If the detachment expands centrally to involve the macula—the specialized central region responsible for high-acuity, color vision—central visual acuity drops precipitously.
Mechanics of Photoreceptor Decay and Need for Emergency Intervention
The requirement for rapid, emergency medical intervention in retinal detachment stems from the time-sensitive nature of photoreceptor tissue ischemia. Photoreceptor outer segments depend entirely on the underlying choriocapillaris, accessed through the adjacent retinal pigment epithelium, for oxygenation, glucose delivery, and metabolic waste removal. When subretinal fluid separates the neurosensory retina from the pigment epithelium, this vital metabolic supply chain is abruptly severed. Within hours of physical separation, ischemic cellular stress triggers an apoptotic cascade within photoreceptors and retinal ganglion cells. Prolonged detachment leads to irreversible structural atrophy, outer segment degradation, and permanent loss of visual function. Clinical urgency is especially paramount when the detachment remains "macula-on"—meaning the central macula is still attached—because immediate surgical reattachment can preserve baseline central visual acuity. Conversely, if the macula detaches ("macula-off"), post-operative visual recovery is significantly compromised, even following successful anatomical reattachment.
Diagnostic Evaluation Protocols and Ophthalmic Imaging
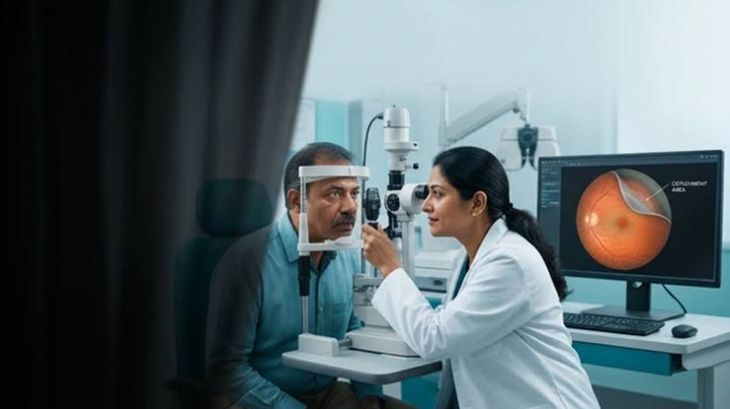
Accurately diagnosing retinal detachment requires an immediate, comprehensive ophthalmic examination. Dilated fundus examination using indirect ophthalmoscopy and scleral depression serves as the cornerstone of evaluation, allowing the clinician to map the full extent of retinal detachment, identify all causative retinal breaks, and assess the presence of proliferative vitreoretinopathy (PVR), a scar-forming cellular response that can complicate reattachment. When dense vitreous hemorrhage or cataract obscures direct visualization of the fundus, ocular B-scan ultrasonography provides crucial diagnostic information by transmitting high-frequency sound waves through the ocular media to map structural posterior segment changes and verify retinal elevation. Optical Coherence Tomography (OCT) yields high-resolution cross-sectional images of the retina, precisely evaluating macular attachment status, subretinal fluid accumulation, and structural layer integrity.
Therapeutic Management and Surgical Reattachment Protocols
Managing rhegmatogenous retinal detachment requires surgical intervention to close all retinal breaks, relieve vitreoretinal traction, and re-establish physical contact between the neurosensory retina and the retinal pigment epithelium. Surgical options depend on the location, size, and complexity of the detachment. Pneumatic retinopexy is a minimally invasive office procedure suitable for uncomplicated superior retinal breaks; it involves injecting an expandable gas bubble into the vitreous cavity to tamponade the tear from within, combined with cryotherapy or laser photocoagulation to seal the retinal edges. Scleral buckling involves encircling the globe with a flexible silicone band, which indents the sclera inward toward the detached retina, relieving vitreoretinaltraction and facilitating subretinal fluid absorption. Pars plana vitrectomy (PPV) is widely utilized for complex, tractional, or inferior detachments. This procedure removes the vitreous gel, releases membrane traction, flattens the retina using heavy liquid or gas, seals breaks with endolaser photocoagulation, and fills the vitreous cavity with a temporary gas or silicone oil tamponade.
Conclusion
Retinal detachment is a sight-threatening ocular emergency driven by the physical separation of the neurosensory retina from the underlying metabolically supportive retinal pigment epithelium. Understanding how vitreoretinal traction, retinal tears, and subretinal fluid accumulation lead to acute photoreceptor ischemia, field defects, and permanent vision loss highlights the critical importance of early recognition. Recognizing early red-flag symptoms—such as sudden light flashes, a shower of floaters, or an advancing visual curtain—enables patients to seek immediate ophthalmic care. Through prompt diagnostic fundus evaluation, ultrasonography, and timely surgical interventions like vitrectomy, scleral buckling, or pneumatic retinopexy, care teams can re-establish retinal alignment, protect macular function, and preserve long-term visual health.