What Is Ebstein Anomaly and How Can It Affect the Heart?
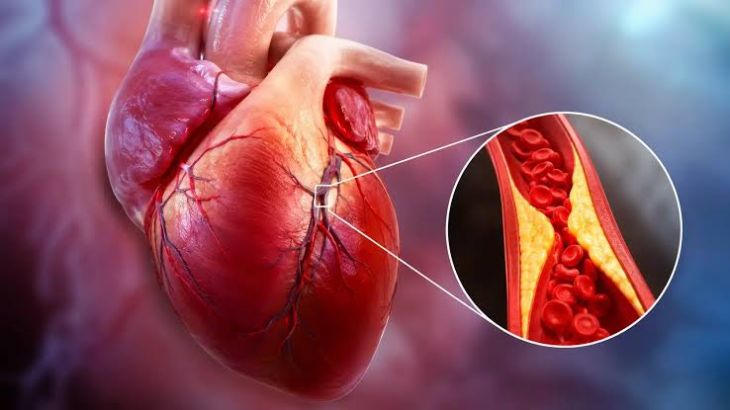
Normal cardiac morphogenesis requires precise spatial alignment, septation, and delamination of the atrioventricular valves to ensure unidirectional, non-turbulent blood flow through the heart. The tricuspid valve complex normally separates the low-pressure right atrium from the right ventricle, consisting of anterior, septal, and posterior leaflets anchored to papillary muscles via chordae tendineae. Ebstein anomaly is a rare, complex congenital heart malformation characterized primarily by failure of delamination of the septal and posterior tricuspid valve leaflets from the underlying right ventricular myocardium. This developmental failure causes apical displacement of the tricuspid valve hinge lines into the right ventricular cavity. Consequently, the anatomical tricuspid orifice shifts downward away from the true atrioventricular junction, structurally dividing the right ventricle into two distinct functional segments and causing marked tricuspid insufficiency, volumetric overload, and progressive cardiac dysfunction.
Pathophysiological Atrialization and Structural Remodeling
The fundamental structural alteration in Ebstein anomaly involves the displacement of the tricuspid valve attachment points toward the cardiac apex. This apical displacement effectively incorporates a significant portion of the inlet zone of the right ventricle into the right atrium, a process known as atrialization of the right ventricle. The atrialized right ventricle becomes thin-walled, dyskinetic, and anatomically continuous with the true right atrium, creating a enlarged combined atrial cavity. Meanwhile, the remaining functional right ventricle is reduced in volume and capacity, consisting primarily of the trabecular and outflow tract regions. During ventricular systole, the large, deformed anterior leaflet—often describe as sail-like—fails to coapt properly with the apically displaced septal and posterior leaflets. This malcoaptation leads to severe tricuspid regurgitation, causing massive right atrial enlargement, elevated right-sided filling pressures, and structural remodeling of the entire right heart.
Hemodynamic Alterations and Interatrial Shunting Dynamics
The combination of severe tricuspid regurgitation, reduced functional right ventricular volume, and impaired right ventricular compliance markedly alters global cardiovascular hemodynamics. As the right atrium expands to accommodate both systemic venous return and regurgitant flow, right-sided filling pressures rise significantly. To relieve this chronic pressure and volume load, the heart frequently maintains or creates an interatrial communication, such as a patent foramen ovale or an atrial septal defect, which is present in up to eighty percent of individuals with Ebstein anomaly. Elevated right atrial pressure relative to left atrial pressure favors a right-to-left interatrial shunt. While this shunt decompresses the congested right atrium, it allows deoxygenated systemic venous blood to mix directly into the left atrium, leading to systemic arterial hypoxemia, cyanosis, exercise intolerance, and an increased risk of paradoxical thromboembolism.
Electrophysiological Instability and Conduction Abnormalities
In addition to severe mechanical and structural deficits, Ebstein anomaly is strongly associated with profound electrophysiological instability. The chronic stretching, fibrosis, and hypertrophy of the atrialized right ventricle and right atrium create an ideal arrhythmogenic substrate for re-entrant electrical circuits. Atrial tachyarrhythmias, including atrial fibrillation, atrial flutter, and focal atrial tachycardia, occur frequently as right atrial dilation progresses. Furthermore, structural disruption at the right atrioventricular junction frequently leads to persistent accessory electrical pathways that bypass the normal atrioventricular node. Ebstein anomaly exhibits a well-documented association with Wolff-Parkinson-White syndrome. The presence of accessory pathways exposes patients to paroxysmal supraventricular tachycardia and sudden cardiac death if rapid atrial impulses are conducted directly to the ventricles over an accessory tract.
Clinical Presentation and Diagnostic Evaluation Protocols
The clinical spectrum of Ebstein anomaly varies widely based on the degree of tricuspid leaflet displacement, the extent of right ventricular impairment, and the presence of associated cardiac defects. Severe cases present during fetal life or the immediate neonatal period with profound cyanosis, massive cardiomegaly, and severe right-sided heart failure. Conversely, milder forms may remain undetected until adolescence or adulthood, presenting insidiously with exertional dyspnea, fatigue, peripheral edema, cyanosis, or symptomatic palpitations. Physical examination typically reveals a widely split first and second heart sound, a prominent third or fourth heart sound, and a pansystolic murmur of tricuspid regurgitation best heard at the lower left sternal border. Diagnostic evaluation relies heavily on transthoracic echocardiography to quantify leaflet displacement, assess functional right ventricular size, measure regurgitant severity, and evaluate interatrial shunting. Cardiac Magnetic Resonance (CMR) imaging provides precise volumetric quantification of right ventricular function and myocardial fibrosis.
Therapeutic Management and Surgical Intervention Strategies
Managing Ebstein anomaly requires a tailored approach that addresses mechanical incompetence, heart failure symptoms, cyanosis, and electrophysiological instability. Medical therapy focuses on managing right heart failure with diuretics, optimizing hemodynamics, and controlling arrhythmias using antiarrhythmic agents or anticoagulation for stroke prevention. In patients with accessory pathways or symptomatic tachyarrhythmias, invasive electrophysiological mapping and catheter ablation serve as crucial interventions. When severe tricuspid regurgitation, progressive right ventricular enlargement, or worsening functional capacity develops, surgical intervention is indicated. Surgical techniques prioritize tricuspid valve repair rather than replacement whenever feasible, utilizing procedures like the cone reconstruction—which mobilizes and rotates the anterior and posterior leaflets to construct a functional valve at the true annulus level. Plication of the atrialized right ventricle, closure of interatrial defects, and concurrent arrhythmia surgery (such as the Maze procedure) are routinely performed during the repair.
Conclusion
Ebstein anomaly is a complex congenital cardiac condition defined by apical displacement of the tricuspid valve leaflets and functional atrialization of the right ventricle. Understanding how this developmental structural defect induces severe tricuspid regurgitation, right-to-left interatrial shunting, ventricular dysfunction, and accessory pathway-mediated arrhythmias clarifies the clinical manifestations and cardiovascular risks experienced by affected individuals. Utilizing comprehensive echocardiography, cardiac MRI, and electrophysiological testing allows specialized multidisciplinary teams to accurately grade disease severity and monitor structural progression. Through targeted medical management, catheter ablation of arrhythmogenic pathways, and timely surgical valve reconstruction, healthcare professionals can successfully alleviate hemodynamic strain, mitigate sudden cardiac risks, and improve long-term functional outcomes for patients living with this condition.