The Dynamic Architecture of Human Skeletal Tissue
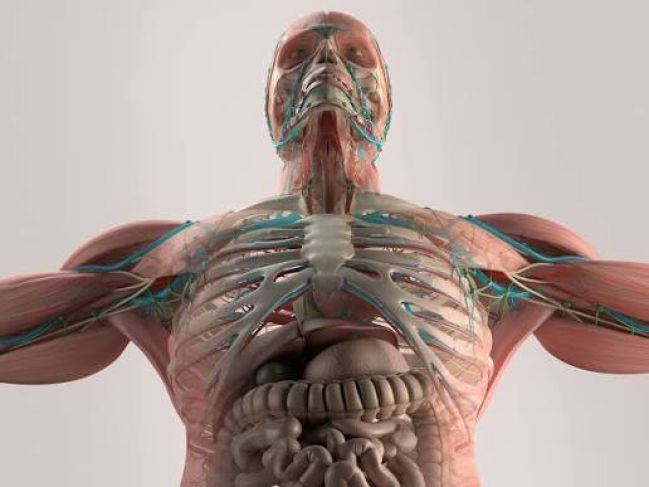
Far from being an inert scaffold of calcium and collagen, the human skeleton is a living, metabolically active organ system in a continuous state of renewal. Throughout life, bone tissue participates in an unending cycle known as bone remodeling, wherein microscopic areas of older, mechanically fatigued bone are methodically resorbed and replaced by freshly synthesized, mineralized matrix. Under healthy physiological conditions, the activities of specialized bone-dissolving cells called osteoclasts and bone-forming cells termed osteoblasts operate in harmonious equilibrium, preserving overall skeletal mass and maintaining tight regulation over systemic calcium reserves.
However, as individuals age or encounter metabolic derangements, this delicate balance frequently tips toward excessive breakdown. Accelerated osteoclastic activity outpaces new matrix deposition, resulting in progressive microarchitectural deterioration, skeletal porosity, and an elevated vulnerability to debilitating fractures. To halt this silent structural degradation, modern clinical medicine relies heavily on a distinct class of antiresorptive pharmacological agents known as bisphosphonates. By directly targeting the cellular mechanics of osteoclasts, these medications stabilize bone mineral density, reduce fracture risk, and help manage complex skeletal conditions, making them a cornerstone of long-term bone health management.
Molecular Structure and Mechanism: How Bisphosphonates Halt Bone Breakdown
The pharmacological effectiveness of bisphosphonates stems from their unique chemical architecture, which directly mirrors endogenous inorganic pyrophosphate—a naturally occurring regulator of calcium metabolism. While pyrophosphate features an oxygen atom linking two phosphate groups, bisphosphonates replace this oxygen with a non-hydrolyzable carbon atom, producing a distinctive phosphorus-carbon-phosphorus backbone. This modified core exhibits an extraordinary chemical affinity for hydroxyapatite crystals, the primary mineral component of vertebrate bone.
Upon entering systemic circulation, bisphosphonate molecules rapidly migrate toward the skeletal surface, selectively concentrating in microenvironments undergoing active remodeling. As osteoclasts attach to the mineralized surface and begin secreting acidic compounds and proteolytic enzymes to excavate bone pits, they inadvertently absorb these bound bisphosphonate molecules via endocytosis. Once internalized within the osteoclast’s cytoplasm, the therapeutic compound disrupts critical cellular machinery, effectively halting the cell's destructive potential.
Modern nitrogen-containing bisphosphonates—including alendronate, risedronate, ibandronate, and zoledronic acid—exert their clinical potency by inhibiting a pivotal intracellular enzyme known as farnesyl pyrophosphate synthase within the mevalonate pathway. This enzymatic blockade prevents the prenylation of essential signaling proteins such as Ras, Rho, and Rac, which are vital for maintaining the osteoclast's ruffled border, cytoskeletal polarization, and survival signaling. Deprived of functional anchorage, the osteoclast ceases its resorptive excavation and undergoes premature apoptosis, or programmed cell death. By curbing excessive osteoclastic turnover, the rate of bone resorption drops precipitously, allowing osteoblastic bone formation to restore matrix density over subsequent months.
Clinical Applications: Major Bone Pathologies Managed by Bisphosphonates
Because of their targeted antiresorptive capacity, bisphosphonates serve as frontline therapies across a diverse spectrum of metabolic, genetic, and oncological bone disorders characterized by accelerated skeletal resorption.
-
Postmenopausal and Age-Related Osteoporosis: The most widespread application of bisphosphonates involves mitigating postmenopausal bone loss driven by estrogen deficiency, as well as age-related senile osteoporosis in older adults. By slowing the accelerated bone turnover that leaves trabecular bone thin and brittle, these agents significantly reduce the incidence of vertebral compression fractures, wrist fractures, and catastrophic hip fractures.
-
Glucocorticoid-Induced Osteoporosis: Prolonged systemic corticosteroid therapy, widely prescribed for autoimmune conditions and inflammatory lung diseases, suppresses osteoblast activity while extending osteoclast longevity. Co-administering bisphosphonates acts as a protective shield, preserving bone density during prolonged steroid exposure.
-
Paget's Disease of Bone: This chronic skeletal condition involves localized regions of frantic, disorganized bone remodeling that produce enlarged, structurally weak, and deformed bone tissue prone to bowing and microfractures. High-potency bisphosphonates, particularly intravenous zoledronic acid, normalize this aberrant cellular turnover, alleviating localized bone pain and halting skeletal deformities.
-
Malignancy-Associated Skeletal Complications: Advanced cancers—particularly breast, prostate, and multiple myeloma—frequently establish metastatic footholds within the bone marrow cavity, triggering severe local bone destruction, pathological fractures, and severe bone pain.
Administration Routes, Formulations, and Dosing Schedules
To accommodate varied clinical needs and patient tolerance profiles, bisphosphonates are engineered in both oral and intravenous formulations, featuring dosing schedules that range from daily regimens to annual infusions.
Oral formulations represent the most common outpatient choice for standard osteoporosis management. Medications such as oral alendronate and risedronate are commonly taken as convenient once-weekly tablets, whereas oral ibandronate offers a monthly dosing schedule. Because the oral bioavailability of bisphosphonates is naturally low—typically less than one percent of the ingested dose crosses the intestinal epithelium—strict administration rules must be followed. Patients must swallow the tablet immediately upon waking with a full glass of plain water, on an empty stomach, and remain strictly upright for at least thirty to sixty minutes without consuming food, beverages, or other medications to maximize absorption and prevent irritation.
Intravenous formulations bypass the gastrointestinal tract entirely, providing a reliable alternative for patients who suffer from esophageal inflammation, experience severe gastrointestinal intolerance, or struggle with strict oral adherence. Intravenous ibandronate is typically administered once every three months, while intravenous zoledronic acid is delivered as a concise annual infusion for osteoporosis, or administered monthly when treating advanced bone metastases. These long-acting parenteral regimens guarantee consistent drug delivery and continuous suppression of bone resorption without requiring weekly attention.
Safety Considerations, Adverse Effects, and Drug Holidays
While bisphosphonates are generally well tolerated and have a long history of clinical use, their powerful suppression of bone turnover requires careful clinical oversight and patient education.
The most frequent side effects associated with oral bisphosphonates involve gastrointestinal distress, including esophageal irritation, acid reflux, epigastric discomfort, and shallow esophageal ulcerations. These local complications generally arise when tablets linger against the delicate esophageal mucosa rather than traveling promptly into the stomach cavity, reinforcing the necessity of taking the medication with ample water and remaining upright. For intravenous infusions, the most common acute adverse reaction is a transient, flu-like response known as the acute-phase reaction, which presents as mild fever, myalgias, and fatigue during the first twenty-four to forty-eight hours post-infusion.
With long-term therapy spanning beyond three to five years, two rare but serious clinical concerns warrant attention:
-
Osteonecrosis of the Jaw (ONJ): Characterized by exposed, non-healing necrotic bone in the maxillofacial region, ONJ occurs primarily in oncology patients receiving high-dose, frequent intravenous infusions rather than standard osteoporosis doses. It is often triggered by invasive dental extractions or deep oral surgery, making preventive dental care essential before starting therapy.
-
Atypical Femoral Fractures (AFF): Prolonged, continuous suppression of skeletal remodeling over many years can theoretically prevent the natural clearance of micro-damage, leading to stress fractures along the lateral subtrochanteric shaft of the femur. Patients presenting with persistent thigh or groin discomfort require prompt radiographic imaging.
To minimize the likelihood of these rare long-term complications while preserving structural benefits, physicians frequently incorporate a structured strategy known as a bisphosphonate drug holiday. Because bisphosphonates bind tightly to bone mineral and possess an exceptionally long biological half-life, their antiresorptive protection persists for years after stopping the medication. After three to five years of continuous therapy, patients deemed to be at moderate fracture risk may temporarily pause treatment, resuming therapy only if serial dual-energy X-ray absorptiometry (DEXA) scans show progressive bone mineral decline.
Conclusion: Balancing Skeletal Strength and Longevity
Bisphosphonates remain one of the most effective and extensively validated pharmacological classes in modern metabolic bone medicine. By selectively targeting and downregulating hyperactive osteoclasts, these therapies halt structural decline, restore stability to porous bone, and dramatically decrease the risk of life-altering fractures in vulnerable populations.
Achieving optimal outcomes with bisphosphonates requires a balanced, patient-centered approach. Strict adherence to proper oral dosing techniques, routine monitoring of bone density metrics, collaborative dental planning, and the timely use of drug holidays allow healthcare providers to maximize bone protection while minimizing clinical risks. When integrated alongside sufficient dietary calcium intake, optimal vitamin D levels, and regular weight-bearing exercise, bisphosphonates provide an enduring foundation for strong, resilient bones throughout life.