Corticobasal Syndrome: Pathophysiology, Neurodegeneration, and Medical Capabilities
Creation to Corticobasal Syndrome and Significant Neurodegeneration
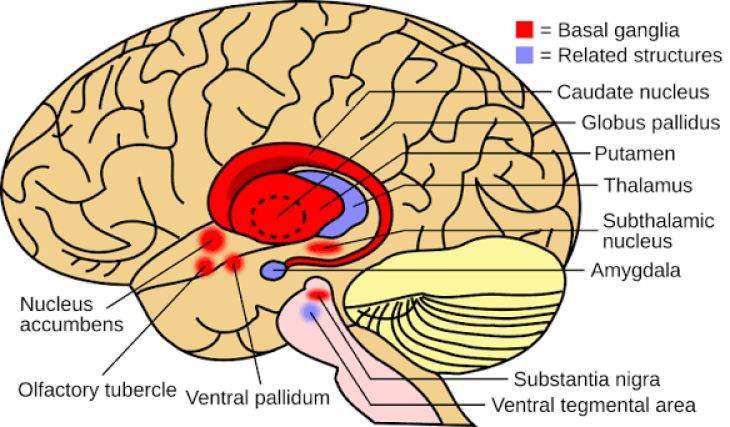
Easy voluntary motion relies upon upon steady neural crosstalk connecting better-order cerebral neocortical fields with subcortical basal ganglia networks. Corticobasal Syndrome is a rare, bizarre parkinsonian situation marked via chronic cell decay across both the cerebral mantle and subcortical motor pathways. Previously regarded only as an extrapyramidal motion condition, present day clinical consensus classifies it as a complex neurodegenerative entity as a result of asymmetrical frontoparietal tissue loss combined with nigrostriatal tract breakdown. The signature hallmark of this pathology is its mentioned clinical lateralization: physical and cognitive impairments emerge overwhelmingly on a single aspect of the body before slowly regarding the other facet. This blended cortical and subcortical damage seriously disrupts guide skill, motor planning, and complicated cognitive processing.
Histological Substrates and Cellular Tau Dynamics
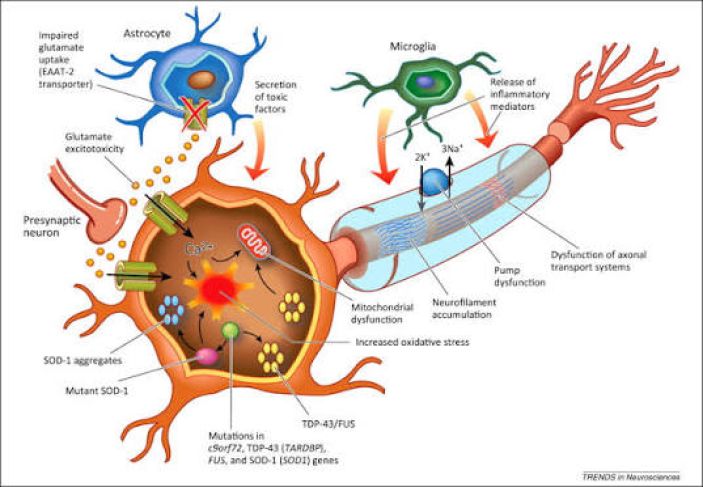
On the mobile stage, corticobasal syndrome maximum regularly arises from an underlying tauopathy referred to as corticobasal degeneration. This pathological kingdom includes hyperphosphorylation and intracellular accumulation of the microtubule-binding protein tau inside neurons, astrocytic strategies, and oligodendrocytes. Beneath wholesome conditions, regular tau molecules stabilize the axonal internal cytoskeleton, making sure green nutrient delivery alongside the axon. When pathological hyperphosphorylation happens, changed tau detaches from microtubules, forming poisonous insoluble aggregates that disrupt intracellular delivery, impair synaptic transmission, and trigger programmed neuronal demise. Histopathological examination demonstrates swollen achromatic neurons (ballooned cells) along wonderful astrocytic plaques concentrated in the frontal and parietal lobes as well as deep grey nuclei. Although number one tauopathy accounts for maximum instances, identical scientific capabilities also can be brought about with the aid of underlying Alzheimer's pathology, revolutionary supranuclear palsy, or frontotemporal lobar degeneration.
Asymmetric Extrapyramidal Features and Motor Impairment
The motor manifestations of corticobasal syndrome are usually lateralized and generally fail to improve with fashionable levodopa substitute remedy. Initial complaints typically involve unilateral stiffness, slowness of motion, and practical clumsiness in one higher extremity. Over the years, the affected arm grows an increasing number of inflexible, immune to passive extension, and might lock right into a persistent dystonic function with a flexed wrist and clenched hand. Simultaneously, subcortical basal ganglia degradation triggers cortical myoclonus—unexpected, brief, surprise-like muscular twitches provoked via motion or light contact—along stability deficits and a gradual, unsteady gait. As those extrapyramidal signs and symptoms progress, easy each day duties like buttoning apparel, dealing with ingesting utensils, or holding gadgets end up impossible without help.
Higher-Order Cortical Deficits and Sensory Agnosia
Beyond subcortical stress, this situation damages parietal and frontal cortical circuits that govern excessive-degree motor making plans and sensory integration. A first-rate cortical deficit is limb apraxia, in which an person loses the ability to carry out learned, purposeful motor sequences notwithstanding retaining ok muscle energy and primary sensation. Affected individuals are not able to demonstrate routine gestures, consisting of using a hairbrush or waving farewell. Any other hanging feature is cortical sensory loss, where the mind can not synthesize sensory enter, leading to an lack of ability to become aware of handheld gadgets by way of touch alone or understand numbers traced onto the pores and skin. In severe instances, sufferers show off the alien limb phenomenon, a surreal sensation where the affected arm executes autonomous, unprompted actions with out aware rationale.
Cognitive Impairment and Behavioral Alterations
As neurodegeneration spreads into prefrontal networks, patients increase distinct cognitive and behavioral modifications. Government disorder often appears early, leading to problem with venture organizing, abstract hassle solving, working reminiscence, and mental flexibility. Speech and language impairments also are common, supplying as non-fluent primary revolutionary aphasia with gradual, hesitant speech output, or as speech apraxia, wherein the motor coordination required for clean articulation breaks down. Innovative parietal lobe atrophy can also reason visuospatial disorientation and spatial navigation problems. Moreover, frontotemporal circuit disruption might also trigger behavioral shifts, along with apathy, emotional blunting, melancholy, or loss of social restraint.
Diagnostic Biomarkers and Imaging Modalities
Setting up a clear scientific analysis for the duration of life stays hard because corticobasal syndrome stocks overlapping functions with different bizarre parkinsonian situations, which includes revolutionary supranuclear palsy, multiple device atrophy, and dementia with Lewy our bodies. Diagnostic protocols blend specific bedside neurological checking out with neuroimaging studies. Structural Magnetic Resonance Imaging typically demonstrates marked, asymmetric cortical shrinkage localized to the frontoparietal cortex opposite the most impaired limb, together with secondary lateral ventricular expansion. Useful metabolic imaging, consisting of Positron Emission Tomography with fluorodeoxyglucose, confirms distinct uneven discount in glucose metabolism throughout the affected cortical regions and basal ganglia. Laboratory testing of cerebrospinal fluid and amyloid imaging help differentiate primary tau-primarily based disease from underlying Alzheimer's versions.
Clinical Management and Palliative Interventions
Presently, no disease-modifying drug exists to halt or reverse the progression of corticobasal syndrome. Clinical interventions awareness on symptom alleviation, preserving purposeful potential where possible, and providing supportive care. A trial of levodopa is robotically performed for stress, even though lengthy-term benefit is uncommon. Focal muscle spasticity and painful dystonia are controlled using oral muscle relaxants, oral clonazepam for myoclonus, or localized botulinum toxin injections immediately into overactive muscle agencies. Physical and occupational treatment options are essential for keeping joint mobility, stopping contractures, and enhancing dwelling areas for safety. Speech therapy allows cope with swallowing safety and communication demanding situations, while caregiver counseling stays vital during the disorder route.
Conclusion
Corticobasal Syndrome is a challenging, innovative neurodegenerative situation defined by way of asymmetrical cortical and subcortical tissue damage. Expertise how tau protein misfolding results in unilateral pressure, limb apraxia, self reliant limb behavior, and govt cognitive decline clarifies the organic underpinnings of this sickness. Utilizing structural MRI, practical pet imaging, and complete neurological critiques allows scientific teams to make well timed diagnoses, manipulate signs efficiently, and implement compassionate guide strategies for affected people.