What Is Encephalopathy and How Can It Affect Brain Function?
The human brain is an exquisitely sensitive metabolic organ that requires a meticulously regulated internal environment to maintain normal consciousness, cognitive processing, memory, and voluntary movement. Unlike localized neurological conditions such as a stroke or a focal brain tumor, which disrupt specific anatomical pathways, certain systemic disorders compromise the entire central nervous system simultaneously. When metabolic imbalances, circulating toxins, systemic infections, or severe oxygen deprivation disrupt the functional integrity of the entire brain without necessarily destroying distinct structural tracts, the resulting condition is known as encephalopathy. Encephalopathy is not a discrete disease in its own right; rather, it is a broad clinical syndrome characterized by altered mental status, cognitive impairment, and global brain dysfunction. Examining the diverse underlying causes and pathophysiological mechanisms of encephalopathy illuminates the profound dependence of cerebral activity on systemic physical health.
Metabolic Encephalopathy and Systemic Chemical Imbalances
One of the most frequent categories of global brain dysfunction encountered in clinical practice is metabolic encephalopathy, which arises when systemic organ failures alter the chemical composition of the blood bathing the central nervous system.
-
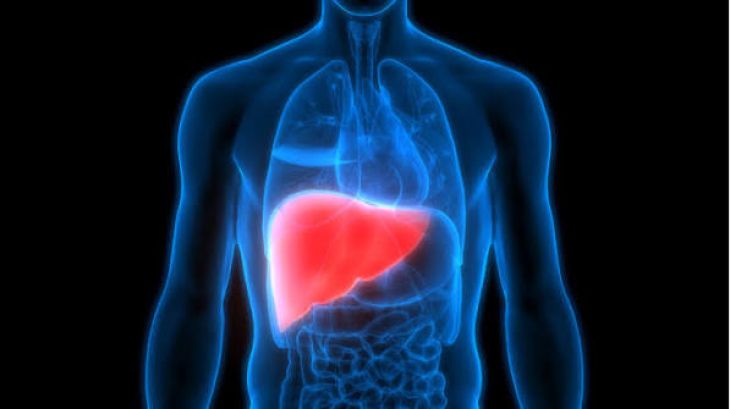
Hepatic Encephalopathy: A classic example is hepatic encephalopathy, occurring in patients with severe liver cirrhosis or acute liver failure. Because a failing liver cannot metabolize and filter nitrogenous waste products like ammonia, these neurotoxins cross the blood-brain barrier, impairing astrocytic function, altering neurotransmitter balance, and inducing widespread cerebral edema and neuronal depression.
-
Uremic Encephalopathy: Similarly, uremic encephalopathy develops in advanced renal failure when unexcreted uremic toxins accumulate in the circulation, disrupting cellular energy metabolism and neural transmission. Other metabolic insults include severe electrolyte disturbances, such as profound hyponatremia or hypercalcemia, and acute glycemic crises like diabetic ketoacidosis, all of which rob neurons of the stable chemical environment required for normal electrical signaling.
Hypoxic-Ischemic Encephalopathy and Cellular Energy Failure
When the entire brain suffers a critical reduction in oxygen delivery or blood perfusion, the resulting global insult precipitates hypoxic-ischemic encephalopathy, one of the most devastating forms of brain dysfunction. This condition frequently occurs following cardiac arrest, severe respiratory failure, carbon monoxide poisoning, or systemic shock.
-
Selective Neuronal Vulnerability: When systemic oxygen levels plummet, neurons throughout the cerebral cortex, hippocampus, and basal ganglia experience immediate cellular energy failure. Deprived of adenosine triphosphate, cellular sodium-potassium pumps fail, causing neurons to depolarize uncontrollably, flood with calcium ions, and unleash destructive enzymatic cascades.
-
Delayed Neuronal Death: This excitotoxic process leads to acute cellular swelling, membrane destruction, and delayed neuronal death. Depending on the duration and severity of the oxygen deprivation, survivors may experience permanent cognitive deficits, persistent vegetative states, or varying degrees of neurological recovery.
Toxic and Pharmacological Encephalopathy
The central nervous system is also exceptionally vulnerable to exogenous chemical agents, leading to toxic or drug-induced encephalopathy when foreign substances or therapeutic medications overwhelm normal metabolic clearance pathways.
-
Substance Overdose: Intentional or accidental overdoses of central nervous system depressants, opioids, sedative-hypnotics, or psychotropic medications can profoundly suppress the reticular activating system in the brainstem, plunging the patient into deep stupor or coma.
-
Heavy Metals and Environmental Toxins: Furthermore, chronic occupational or environmental exposure to heavy metals such as lead, mercury, or arsenic, as well as industrial solvents, can disrupt axonal transport, damage myelin sheaths, and cause progressive cognitive decline and psychiatric disturbances. In clinical settings, iatrogenic toxicity from certain chemotherapeutic agents or long-term antimicrobial therapies can also precipitate acute encephalopathic changes, highlighting the delicate chemical balance required to sustain cognitive clarity.
Infectious and Septic Encephalopathy
Systemic infections remote from the brain can nonetheless exert profound deleterious effects upon cerebral function, a phenomenon widely recognized as septic encephalopathy. When severe bacterial sepsis unleashes a massive systemic inflammatory response, circulating pro-inflammatory cytokines, bacterial endotoxins, and inflammatory mediators cross the blood-brain barrier. This neuroinflammatory cascade alters endothelial function, increases vascular permeability, induces microglial activation, and disrupts neurotransmitter synthesis within the cerebral cortex. Patients suffering from septic encephalopathy experience profound delirium, confusion, lethargy, and attentional deficits even in the complete absence of direct microbial invasion of the brain parenchyma, complicating the clinical management of critically ill individuals.
Clinical Presentation and Spectrum of Altered Mental Status
Because encephalopathy represents a global disruption of brain function, its clinical presentation spans a wide spectrum of cognitive and behavioral abnormalities rather than isolated focal deficits.
-
Early Manifestations: In the earliest stages, individuals may exhibit subtle personality changes, irritability, short-term memory loss, diminished concentration, and subtle inversions of the sleep-wake cycle, where patients sleep during the day and experience agitation at night.
-
Progressive Decline: As the underlying metabolic, toxic, or hypoxic insult worsens, patients progress into pronounced states of acute confusion, disorientation, and fluctuating delirium. In severe cases, encephalopathy deepens into stupor, where the patient responds only to vigorous physical stimuli, and ultimately into profound coma, accompanied by abnormal posturing, loss of protective airway reflexes, and generalized motor flaccidity. Physical examinations may reveal characteristic neurological signs depending on the etiology, such as asterixis—a rhythmic flapping tremor of outstretched hands frequently seen in hepatic or uremic encephalopathies—or generalized hyperreflexia and clonus.
Diagnostic Investigations and Clinical Evaluation
Uncovering the specific root cause of encephalopathy requires a comprehensive diagnostic evaluation, as treatment depends entirely on identifying and reversing the underlying systemic trigger.
-
Laboratory Investigations: Clinicians initiate investigations with extensive blood and metabolic panels to evaluate renal and hepatic function, screen for electrolyte derangements, measure blood glucose levels, analyze arterial blood gases, and check for systemic markers of infection or toxin ingestion.
-
Neuroimaging and Electroencephalography: Furthermore, neuroimaging modalities such as computed tomography or magnetic resonance imaging are performed to rule out structural lesions, acute intracranial hemorrhages, or focal strokes that could mimic global encephalopathy. Electroencephalography plays a vital role by recording continuous brainwave activity, frequently displaying generalized slowing, triphasic waves, or epileptiform discharges that help confirm the presence of metabolic or toxic encephalopathy and exclude non-convulsive status epilepticus.
Management Strategies and Reversibility
Managing encephalopathy centers primarily on identifying, treating, and correcting the primary systemic insult while providing meticulous supportive care to protect the brain from secondary injury.
-
Correction of Metabolic Derangements: For metabolic and toxic encephalopathies, targeted interventions include dialysis for renal failure, lactulose and rifaximin to clear ammonia in hepatic encephalopathy, electrolyte repletion, and the administration of specific reversal agents or antidotes in cases of drug overdose.
-
Supportive Care: Supportive management in intensive care units involves maintaining adequate oxygenation, stabilizing systemic blood pressure, ensuring optimal cerebral perfusion, controlling seizures with antiepileptic medications, and preventing complications associated with prolonged immobility and altered consciousness. When underlying systemic triggers are rapidly corrected, many forms of encephalopathy are fully reversible, allowing patients to regain their baseline cognitive function and neurological health.
Conclusion
Encephalopathy is a complex and multifaceted clinical syndrome characterized by global brain dysfunction resulting from systemic metabolic imbalances, circulating toxins, profound hypoxia, or severe infections. By examining how hepatic failure, uremia, toxic drug exposures, and septic inflammation disrupt the delicate homeostatic environment of the central nervous system, the pervasive vulnerability of the human brain becomes apparent. Through rigorous laboratory investigations, advanced neuroimaging, electroencephalographic monitoring, and aggressive correction of underlying systemic disorders, healthcare providers can successfully reverse acute mental alterations, protect cerebral tissue, and restore long-term cognitive well-being.