Understanding Common Disorders of the Esophagus and Their Symptoms
The human esophagus is a muscular, collapsible conduit measuring approximately twenty-five centimeters in length, designed to transport ingested food and liquids rapidly from the pharynx down into the stomach. Constructed as a specialized muscular tube, the esophagus features an inner mucosal lining composed of protective squamous epithelium and is guarded at both ends by high-pressure zones known as sphincters. The upper esophageal sphincter prevents air from entering the digestive tract during inspiration and stops swallowed material from entering the airway, while the lower esophageal sphincter acts as a critical barrier guarding against the retrograde flow of acidic gastric contents. When food enters the esophagus, a coordinated sequence of progressive, wave-like muscular contractions known as peristalsis propels the bolus downward against gravity. However, when structural weaknesses, neuromuscular dysfunctions, or chronic mucosal irritations compromise this delicate system, individuals experience debilitating esophageal disorders that disrupt normal swallowing and impair nutritional intake.
Gastroesophageal Reflux Disease: Pathophysiology and Mucosal Injury
Among all pathologies affecting the upper gastrointestinal tract, gastroesophageal reflux disease stands out as the most prevalent and clinically significant condition encountered by healthcare providers. This chronic disorder arises primarily when transient inappropriate relaxations of the lower esophageal sphincter—or mechanical weaknesses caused by a hiatal hernia—allow acidic gastric juices, pepsin, and bile salts to wash backward into the delicate squamous lining of the lower esophagus. Because the esophageal epithelium lacks the robust mucous protection found in the stomach, prolonged exposure to these harsh digestive enzymes inflicts continuous chemical irritation. Over time, this repetitive injury triggers basal cell hyperplasia, localized inflammation, and erosive esophagitis. If left unmanaged, chronic mucosal damage can induce metaplastic transformations known as Barrett's esophagus, where normal squamous tissue is replaced by abnormal columnar epithelium, carrying a significantly elevated lifetime risk of developing esophageal adenocarcinoma.
Esophageal Motility Disorders: Achalasia and Spastic Conditions
In addition to reflux-mediated mucosal damage, the esophagus can be severely compromised by primary motility disorders that disrupt the synchronized neuromuscular contractions required for normal swallowing.
-
Achalasia: A classic and severe example is achalasia, a neurodegenerative motility disorder characterized by the selective loss of inhibitory ganglion cells within the myenteric plexus of the esophageal wall. This pathological loss prevents the lower esophageal sphincter from relaxing normally during a swallow, while simultaneously causing a total absence of coordinated peristalsis in the lower two-thirds of the tubular esophagus. Consequently, ingested food and liquids accumulate inside the dilated esophageal lumen, causing progressive difficulty swallowing both solids and liquids.
-
Spastic Esophageal Disorders: Other motility abnormalities include diffuse esophageal spasm and hypercontractile esophagus, where uncoordinated, high-amplitude muscle contractions generate agonizing chest pain that frequently mimics a cardiac heart attack.
Hiatal Hernias: Structural Disruption of the Diaphragmatic Hiatus
The structural integrity of the lower esophageal junction is intimately tied to the diaphragm, a dome-shaped muscular partition separating the thoracic and abdominal cavities. A hiatal hernia develops when a portion of the upper stomach pushes upward through the diaphragmatic hiatus—the opening through which the esophagus passes into the abdomen. There are two primary anatomical types of hiatal hernias: sliding hiatal hernias, where the gastroesophageal junction slides upward into the chest cavity, and paraesophageal hernias, where a portion of the gastric fundus rolls up alongside the esophagus while the gastroesophageal junction remains anchored below the diaphragm. Sliding hernias frequently exacerbate gastroesophageal reflux by disrupting the normal mechanical angle of His and weakening the closing pressure of the lower esophageal sphincter, whereas large paraesophageal hernias carry mechanical risks of gastric volvulus, ischemia, and bowel strangulation, requiring vigilant surgical oversight.
Clinical Symptom Presentation: Dysphagia, Heartburn, and Regurgitation
Esophageal disorders present with a distinct constellation of clinical symptoms that reflect whether the primary underlying pathology involves mucosal inflammation, mechanical obstruction, or neuromuscular failure.
-
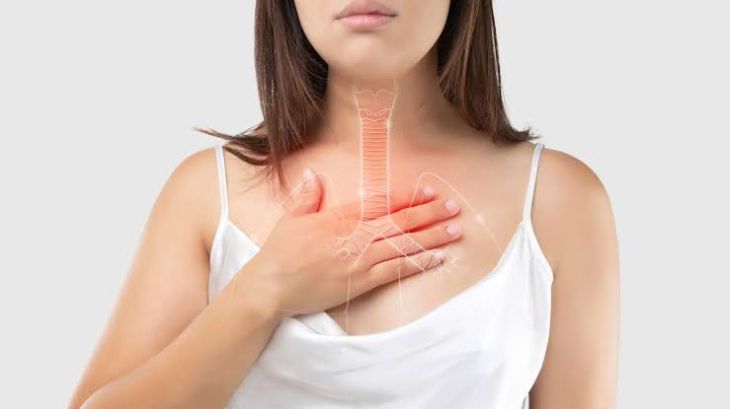
Heartburn and Regurgitation: The hallmark symptom of gastroesophageal reflux disease is a burning sensation radiating upward from the epigastrium behind the sternum, frequently accompanied by the bitter or sour regurgitation of gastric contents into the mouth, especially when bending over or lying flat at night.
-
Dysphagia: A critical symptom spanning multiple esophageal conditions is dysphagia, or difficulty swallowing. Patients with achalasia typically experience dysphagia for both solids and liquids from the onset, whereas individuals with mechanical strictures or esophageal malignancies notice progressive dysphagia that begins primarily with solid foods and gradually worsens to include liquids.
-
Odynophagia and Chest Pain: Other alarming clinical presentations include odynophagia—painful swallowing—often seen in infectious or erosive esophagitis, and non-cardiac chest pain resulting from severe esophageal muscle spasms.
Diagnostic Investigations: Endoscopy, Manometry, and Imaging
Uncovering the specific root cause of esophageal symptoms requires a comprehensive diagnostic evaluation utilizing advanced gastroenterological tools.
-
Upper Endoscopy: Upper gastrointestinal endoscopy serves as the primary diagnostic modality, allowing gastroenterologists to visualize the mucosal lining of the esophagus directly, identify erosive esophagitis, detect hiatal hernias, take tissue biopsies to diagnose Barrett's esophagus or dysplasia, and dilate benign strictures.
-
Esophageal Manometry and pH Monitoring: When motility disorders are suspected, high-resolution esophageal manometry is performed to measure pressures and assess peristaltic coordination along the entire length of the esophagus. Furthermore, ambulatory 24-hour pH or impedance monitoring provides precise quantitative data on acid exposure and reflux episodes, confirming the diagnosis of gastroesophageal reflux disease in complex or atypical cases.
Therapeutic Interventions and Management Strategies
Managing esophageal disorders requires targeted strategies tailored specifically to the underlying mechanism of disease, ranging from lifestyle modifications and potent antisecretory medications to advanced endoscopic and surgical interventions.
-
Medical and Lifestyle Management for GERD: Patients with gastroesophageal reflux disease are advised to modify lifestyle factors—such as elevating the head of the bed, avoiding late-night meals, and eliminating dietary triggers like caffeine, alcohol, and fatty foods—while taking pharmaceutical agents such as proton pump inhibitors or H2-receptor antagonists to suppress gastric acid production and promote mucosal healing.
-
Interventions for Motility Disorders and Hernias: For conditions like achalasia, treatments focus on disrupting the tight lower esophageal sphincter through pneumatic dilation, targeted botulinum toxin injections, or myotomy procedures, while paraesophageal and large sliding hiatal hernias often require surgical repair to reposition the stomach and reinforce the diaphragmatic hiatus.
Conclusion
Esophageal disorders encompass a wide spectrum of conditions—ranging from reflux-induced mucosal injury and Barrett's esophagus to neuromuscular motility failures like achalasia and structural hiatal hernias—that significantly impair swallowing and reduce quality of life. By examining how sphincter dysfunction, mucosal acid exposure, and myenteric nerve degeneration disrupt the normal physiology of the upper gastrointestinal tract, the critical importance of accurate clinical evaluation becomes evident. Through precise endoscopic visualization, high-resolution manometric testing, acid suppression therapy, and targeted surgical interventions, healthcare providers can successfully alleviate distressing symptoms, heal mucosal tissues, and restore normal digestive function for affected individuals.