What Is Ataxia-Telangiectasia and How Does It Affect the Brain and Nervous System?
The preservation of neuronal architecture and central nervous system integrity relies on continuous, high-fidelity DNA repair mechanisms. Nerve cells, particularly post-mitotic neurons, encounter constant endogenously and exogenously generated DNA damage from oxidative stress, metabolic byproducts, and ionizing radiation. To combat this, human cells employ a complex network of signaling molecules collectively termed the DNA damage response (DDR). Ataxia-Telangiectasia (AT), historically known as Louis-Bar syndrome, is a complex autosomal recessive neurodegenerative and immunodeficiency disorder caused by mutations in the ATM (Ataxia-Telangiectasia Mutated) gene. The disease is characterized clinically by progressive cerebellar ataxia, oculocutaneous telangiectasias, profound cellular and humoral immunodeficiency, extreme sensitivity to ionizing radiation, and a heightened predisposition to lymphoid malignancies. Within the nervous system, impaired ATM signaling triggers continuous oxidative stress, defective DNA repair, and targeted degeneration of cerebellar Purkinje and granule neurons.
Genetics and Molecular Mechanics of the ATM Protein Kinase
The molecular etiology of Ataxia-Telangiectasia centers on pathogenic mutations in the ATM gene located on chromosome 11q22.3. The ATM gene encodes a large serine/threonine protein kinase belonging to the phosphatidylinositol 3-kinase-related kinase (PIKK) family. Under physiological conditions, the ATM kinase exists as an inactive homodimer. When a double-strand break occurs, the MRN protein complex (composed of MRE11, RAD50, and NBN) recognizes the DNA lesion and recruits inactive ATM homodimers to the site of damage. Autophosphorylation at serine-1981 disassociates the dimer into active ATM monomers. Active ATM phosphorylate hundreds of downstream substrate targets, including p53, CHK2, BRCA1, and H2AX. This signaling cascade halts the cell cycle at G1/S, S, or G2/M checkpoints to allow time for DNA repair via homologous recombination or non-homologous end joining. If repair fails, ATM signaling triggers programmed cell death (apoptosis). In patients with Ataxia-Telangiectasia, loss-of-function mutations eliminate or severely disrupt ATM kinase activity, preventing effective double-strand break repair and allowing unrepaired DNA lesions and chromosomal instability to accumulate rapidly.
Pathophysiology of Cerebellar Degeneration and Purkinje Cell Loss
Although ATM is expressed throughout systemic tissues, the central nervous system—and specifically the cerebellum—exhibits exceptional vulnerability to loss of ATM function. Within the cerebellar cortex, Purkinje cells serve as the sole inhibitory output drivers integrating motor control signals. Purkinje cells possess high metabolic activity and consume substantial oxygen, generating significant intracellular reactive oxygen species (ROS). Beyond its role in nuclear DNA repair, the ATM protein kinase acts as a direct sensor of cytoplasmic oxidative stress and maintains mitochondrial homeostasis. Loss of ATM disrupts mitochondrial quality control (mitophagy), leading to the accumulation of dysfunctional mitochondria, persistent reactive oxygen species elevation, and cytoplasmic lipid peroxidation. Concurrently, unrepaired DNA double-strand breaks induce severe genomic stress within Purkinje cells and cerebellar granule neurons. Because Purkinje cells are post-mitotic and cannot re-enter the cell cycle, continuous oxidative and genomic strain triggers progressive, non-apoptotic cell death. Pathologically, the cerebellar cortex undergoes profound atrophy, characterized by severe loss of Purkinje cells, marked thinning of the granular layer, and widespread gliosis.
Progressive Motor Dysfunction and Extrapyramidal Mechanics
The selective degeneration of cerebellar circuits produces the cardinal neurological manifestation of Ataxia-Telangiectasia: progressive truncal and appendicular ataxia. Initial neurological symptoms typically manifest in early childhood, around one to two years of age, when affected children begin to walk. Parents observe an unsteady, wide-based gait, frequent falls, and postural instability. As cerebellar degeneration advances, truncal ataxia worsens, causing affected children to lose the ability to sit or stand unassisted, usually necessitating wheelchair dependence by ten to twelve years of age. Dysmetria, dysdiadochokinesia, and intention tremors severely impair fine motor tasks such as writing, dressing, and eating. As the disease progresses beyond the cerebellar cortex into the basal ganglia and brainstem pathways, extrapyramidal movement disorders emerge. Patients develop choreoathetosis (involuntary writhing movements), dystonic posturing, resting tremors, and parkinsonian rigidity. Furthermore, degeneration of bulbar motor nuclei induces progressive dysarthria (producing slow, slurred, and scanning speech) and dysphagia, increasing the risk of aspiration pneumonia.
Oculomotor Apraxia and Cutaneous Telangiectasia Mechanics
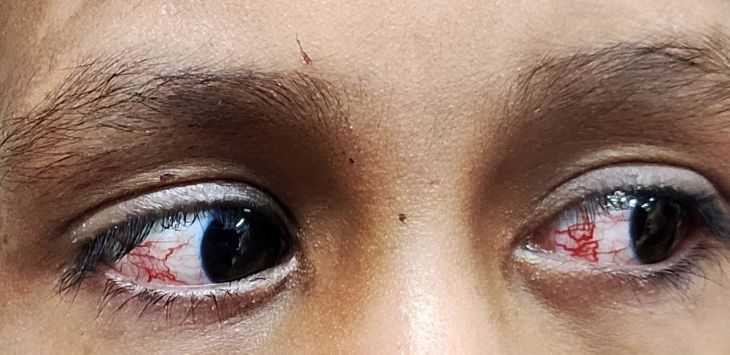
A highly characteristic neuro-ophthalmologic hallmark of Ataxia-Telangiectasia is oculomotor apraxia—the inability to initiate voluntary saccadic eye movements toward a target. When asked to look at an object in the peripheral visual field, affected individuals cannot rapidly shift their gaze; instead, they display compensatory head thrusts, overshooting the target with their head to drag their eyes along, followed by slow ocular drift back to center. Fixation nystagmus, pursuit movement impairment, and strabismus are also common. Non-neurological manifestations develop in parallel, most notably oculocutaneous telangiectasias. Telangiectasias are dilated, tortuous venules that typically appear between three and six years of age. They manifest first on the bulbar conjunctiva of the eye, presenting as prominent bloodshot vessel loops, and subsequently spread to sun-exposed cutaneous areas, including the bridge of the nose, ears, neck, and flexor surfaces of the extremities.
Diagnostic Protocols, Laboratory Markers, and Clinical Evaluation
Establishing an accurate diagnosis of Ataxia-Telangiectasia requires integrating clinical neurological assessments, specialized biochemical markers, and genetic testing. Serum Alpha-Fetoprotein (AFP) serves as the primary diagnostic biomarker; elevated serum AFP levels (exceeding normal age-adjusted ranges) are present in over ninety-five percent of affected individuals due to hepatic gene derepression resulting from chromatin instability. Immunological profiling reveals immunodeficiency, characterized by low or absent serum IgA, IgG2, and IgE levels, alongside variable T-cell lymphopenia. Cytogenetic analysis reveals elevated chromosomal breakage, particularly reciprocal translocations involving chromosomes 7 and 14 within lymphocyte cultures. Diagnostic confirmation is achieved through immunoblotting demonstrating absent or markedly reduced ATM protein levels in cultured lymphoblasts, paired with next-generation sequencing confirming biallelic pathogenic mutations in the ATM gene. Brain Magnetic Resonance Imaging (MRI) reveals progressive, isolated cerebellar atrophy with expansion of the primary cerebellar fissures and fourth ventricle, while supratentorial structures typically remain preserved during early diseasestages.
Therapeutic Management, Radiation Safety, and Multidisciplinary Care
Currently, there is no cure or disease-modifying therapy capable of reversingthe progressive neurodegeneration of Ataxia-Telangiectasia. Clinical management focuses on supportive care, symptom suppression, immunodeficiency oversight, and rigorous monitoring for malignancy. Physical therapy maintains joint mobility and delays contractures, while occupational therapy provides adaptive equipment to preserve functional autonomy. Speech and language therapy supports communication and evaluates swallow safety to prevent aspiration. Because ATM deficiency causes extreme radiosensitivity, exposure to diagnostic ionizing radiation (such as conventional radiographs or CT scans) must be strictly minimized, and radiomimetic chemotherapy agents or radiotherapy are strictly contraindicated or modified during cancer treatment to prevent fatal tissue necrosis. Immunodeficiency requires proactive administration of prophylactic antibiotics and periodic intravenous or subcutaneous immunoglobulin (IVIG) replacement therapy.
Conclusion
Ataxia-Telangiectasia is a severe autosomal recessive neurodegenerative disorder driven by mutations in the ATM gene, which disrupt DNA double-strand break repair, antioxidant defenses, and mitochondrial maintenance. Understanding how ATM loss triggers oxidative stress, Purkinje cell loss, and cerebellar cortical atrophy clarifies the mechanical progression from early infantile gait instability to severe truncal ataxia, oculomotor apraxia, and extrapyramidal dyskinesias. Utilizing serum alpha-fetoprotein quantification, immunoglobulins screening, brain MRI, and ATM gene sequencing enables clinical teams to establish an accurate diagnosis early. Through dedicated physical and speech rehabilitation, careful radioprotection, immunomodulatory support, and multidisciplinary coordination, healthcare professionals can effectively manage neurological complications and improve the quality of life for affected individuals.