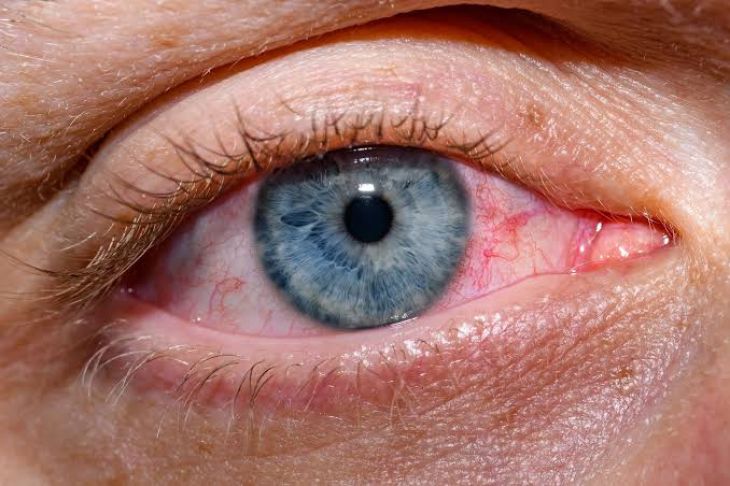
Understanding Common Disorders of the Lacrimal Glands and Tear Production
The maintenance of ocular surface health, optical clarity, and visual comfort depends entirely on the continuous production and precise distribution of the lacrimal tear film. The main lacrimal gland, situated within the lacrimal fossa in the upper outer orbit, along with accessory lacrimal glands, secretes the aqueous component of the tear fluid. This fluid is organized into a highly specialized three-layer structure: an innermost mucin layer produced by conjunctival goblet cells, a middle aqueous layer containing water, electrolytes, and antimicrobial proteins, and an outer lipid layer secreted by the meibomian glands to reduce evaporation. Together, these layers hydrate the cornea, clear metabolic waste, protect against microbial invasion, and preserve a smooth optical interface. Disorders affecting the lacrimal glands or the tear drainage pathway disrupt this balance, leading to persistent surface irritation, visual distortion, and potential corneal damage.
Pathophysiology of Acute and Chronic Dacryoadenitis
Dacryoadenitis refers to the inflammatory or infectious involvement of the main lacrimal gland, presenting as either acute or chronic conditions. Acute dacryoadenitis is most frequently caused by ascending viral or bacterial infections, including mumps, Epstein-Barr virus, Staphylococcus aureus, and Streptococcus species. The condition presents with sudden onset of unilateral orbital pain, erythema, localized edema, and a characteristic S-shaped deformity of the upper eyelid, often accompanied by purulent discharge and localized lymphadenopathy. Conversely, chronic dacryoadenitis is typically non-infectious and arises from systemic autoimmune or granulomatous diseases, such as Sjögren's syndrome, sarcoidosis, IgG4-related disease, or thyroid eye disease. Chronic inflammation leads to progressive lymphocytic infiltration, tissue fibrosis, and eventual atrophy of the glandular acini, compromising the gland's capacity to produce adequate aqueous tear volume.
Aqueous Deficient Dry Eye and Sjögren's Syndrome
Dry Eye Disease represents a widespread, multifactorial ocular surface disorder classified into two primary categories: evaporative dry eye and aqueous deficient dry eye. Aqueous deficient dry eye directly stems from reduced lacrimal gland secretion, preventing the formation of an adequate tear film layer. This deficiency is further divided into Sjögren's and non-Sjögren's subtypes. In Sjögren's syndrome, an autoimmune disorder, immune cells target and destroy exocrine tissues, particularly the lacrimal and salivary glands. Non-Sjögren's aqueous deficiency can result from age-related glandular atrophy, lacrimal duct obstruction secondary to scarring conjunctivitis, neurotrophic corneal hypoesthesia, or systemic medications such as antihistamines, beta-blockers, and antidepressants. The resulting tear deficit causes corneal epithelial breakdown, punctate keratopathy, burning sensations, photophobia, and fluctuating visual acuity that worsens with prolonged visual tasks.
Nasolacrimal Duct Obstruction and Epiphora
While inadequate tear production causes dry eye disease, impaired drainage through the nasolacrimal apparatus produces excessive tearing, known as epiphora. Under physiological conditions, tears flow across the ocular surface, enter the upper and lower puncta, pass through the canaliculi into the lacrimal sac, and drain into the inferior nasal meatus via the nasolacrimal duct. Nasolacrimal duct obstruction can be congenital, caused by a persistent membrane at the Valve of Hasner, or acquired, secondary to chronic involutional stenosis, nasal trauma, dacryolith formation, or sinus inflammation. Blockage within this drainage canal causes tears to overflow onto the cheek, causing skin maceration and blurry vision. Furthermore, stagnant fluid within the obstructed lacrimal sac creates an environment prone to bacterial overgrowth, leading to dacryocystitis—an acute, painful infection of the lacrimal sac characterized by medial canthal swelling, tenderness, and purulent discharge.
Diagnostic Evaluation and Functional Tear Testing
Evaluating lacrimal gland disorders and tear dynamics requires a structured combination of clinical tests and diagnostic imaging. Tear film quantity is routinely measured using Schirmer's test, which utilizes standardized paper strips placed in the lower conjunctival sac to measure fluid production over five minutes. Tear film stability and quality are assessed using tear breakup time (TBUT) following fluorescein dye instillation, where rapid breakdown indicates lipid or mucin layer defects. Ocular surface staining with fluorescein or lissamine green highlights areas of corneal and conjunctival epithelial damage. For drainage abnormalities, lacrimal irrigation and probing verify canalicular patency, while dacryocystography or anterior segment Optical Coherence Tomography (OCT) maps anatomical obstructions along the nasolacrimal pathway. In cases of suspected systemic inflammation or lacrimal gland enlargement, orbital Magnetic Resonance Imaging (MRI) and tissue biopsy provide crucial diagnostic confirmation.
Therapeutic Strategies and Clinical Management
Managing disorders of the lacrimal system focuses on restoring ocular surface hydration, suppressing active inflammation, and re-establishing functional tear drainage. For aqueous deficient dry eye, artificial tears, lubricating ointments, and punctal plugs—which physically block tear drainage to preserve existing fluid—serve as mainstays of conservative therapy. Topical anti-inflammatory agents, such as cyclosporine, lifitegrast, or short courses of corticosteroids, help control lacrimal gland and ocular surface inflammation. Active bacterial infections, like acute dacryoadenitis or dacryocystitis, require targeted systemic antibiotics alongside warm compresses. When conservative measures fail to resolve nasolacrimal duct obstruction, surgical intervention becomes necessary. Congenital cases often respond to minimally invasive probing or balloon dacryoplasty, whereas persistent adult obstructions require dacryocystorhinostomy (DCR) to create a direct bypass route between the lacrimal sac and the nasal cavity.
Conclusion
Disorders of the lacrimal glands and tear production span a broad spectrum of conditions, ranging from inflammatory dacryoadenitis and aqueous deficient dry eye to structural nasolacrimal obstructions. Understanding how disruption across the lacrimal apparatus impairs tear film stability, damages the corneal epithelium, and alters fluid drainage clarifies the mechanisms behind surface irritation, chronic epiphora, and visual fluctuations. Combining quantitative Schirmer testing, tear breakup time analysis, lacrimal irrigation, and advanced neuroimaging enables care teams to pinpoint specific functional or anatomical defects. Through artificial tear supplementation, targeted anti-inflammatory medical therapy, punctal occlusion, or reconstructive surgical bypass, healthcare professionals can effectively restore ocular surface homeostasis, mitigate infection risks, and preserve long-term visual health.