What Is Aortic Regurgitation and How Can It Affect the Heart Over Time?
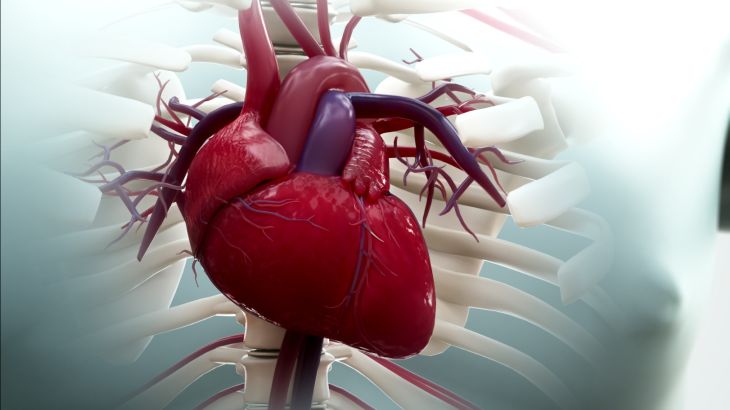
Unidirectional blood flow through the heart is maintained by four specialized cardiac valves that open and close in response to intravascular pressure differentials. The aortic valve, positioned between the left ventricle and the ascending aorta, is a semilunar valve typically comprising three symmetrical cusps or leaflets (the line of closure forming the sinus of Valsalva). During ventricular systole, high intraventricular pressure forces the aortic valve leaflets open, allowing oxygenated blood to eject rapidly into the systemic circulation. During ventricular diastole, as left ventricular pressure falls below aortic pressure, the aortic leaflets approximate tightly, preventing retrograde blood flow back into the left ventricle. Aortic Regurgitation (AR), also referred to as aortic insufficiency, is a structural and functional valvular disorder characterized by the incomplete closure of the aortic valve leaflets during diastole. This incompetence allows a variable portion of the ejected stroke volume to leak backward into the left ventricle, setting off a progressive sequence of hemodynamic alterations, mechanical strain, and structural cardiac remodeling.
Etiology and Structural Mechanisms of Valvular Incompetence
The underlying causes of aortic regurgitation are broadly divided into diseases affecting the aortic valve leaflets themselves and disorders causing primary dilation or distortion of the aortic root and ascending aorta. Primary leaflet pathology includes congenital malformations—most notably a bicuspid aortic valve, where two asymmetrical leaflets replace the normal trileaflet architecture, predisposing the valve to premature calcification, fibrosis, and regurgitation. Rheumatic heart disease, infective endocarditis (which causes leaflet perforation or vegetation-induced malalignment), and senile calcific degeneration represent prominent acquired valvular etiologies. Conversely, aortic root pathology leads to functional aortic regurgitation through loss of leaflet coaptation without primary valvular tissue destruction. Dilation of the aortic annulus or sinotubular junction—seen in thoracic aortic aneurysms, connective tissue disorders such as Marfan syndrome and Ehlers-Danlos syndrome, hypertension, and aortic dissection—stretches the aortic ring, preventing the leaflet edges from meeting during diastole and creating a central regurgitant jet.
Mechanisms of Volume Overload and Eccentric Hypertrophy
The fundamental pathophysiological hallmark of chronic aortic regurgitation is a combined volume and pressure overload imposed on the left ventricle. During diastole, the left ventricle receives blood simultaneously from two sources: normal forward inflow from the left atrium across the mitral valve, and pathological backward inflow leaking from the high-pressure aorta across the incompetent aortic valve. The volume of blood returning to the left ventricle during diastole defines the regurgitant volume, which depends on the effective regurgitant orifice area, the diastolic pressure gradient between the aorta and left ventricle, and the length of diastole. To accommodate this massive influx without precipitously raising end-diastolic pressure, the left ventricle undergoes progressive eccentric hypertrophy. Cardiomyocytes lengthen through the addition of sarcomeres in series, leading to left ventricular chamber dilation. This adaptive mechanism increases left ventricular compliance and end-diastolic volume, allowing the ventricle to generate a high total stroke volume (the sum of forward stroke volume and regurgitant volume) to maintain effective forward cardiac output into systemic circulation.
Hemodynamic Progression from Compensation to Ventricular Failure
For years or even decades, the structural adaptation of eccentric hypertrophy allows the left ventricle to remain compensated, maintaining normal forward cardiac output at rest despite severe regurgitation. However, chronic volume overload imposes extreme wall stress on the myocardium. According to Laplace’s law, wall stress is directly proportional to intraventricular pressure and radius, and inversely proportional to wall thickness. Over time, the compensatory capacity of eccentric hypertrophy reaches its limit. The ratio of wall thickness to chamber radius decreases, leading to excessive systolic wall stress (afterload mismatch). Chronic stretch induces myocardial microvascular ischemia, cellular apoptosis, and interstitial collagen deposition (fibrosis). As intrinsic myocardial contractility declines, left ventricular end-systolic volume increases, ejection fraction drops, and stroke volume falls. Left ventricular end-diastolic pressure rises sharply, transmitting backward through the left atrium and pulmonary veins to induce postcapillary pulmonary hypertension and eventual right ventricular failure.
Clinical Presentation, Peripheral Vascular Signs, and Symptoms
The clinical presentation of aortic regurgitation differs dramatically depending on whether the onset is acute or chronic. Acute aortic regurgitation—often triggered by infective endocarditis, acute type A aortic dissection, or blunt chest trauma—presents as a catastrophic medical emergency. Because the unadapted, non-compliant left ventricle cannot rapidly dilate to accommodate the sudden regurgitant volume, left ventricular end-diastolic pressure surges rapidly, causing acute pulmonary edema, low cardiac output, and cardiogenic shock. In contrast, chronic aortic regurgitation remains asymptomatic for decades due to gradual ventricular adaptation. When symptoms eventually manifest, patients experience exertional dyspnea, fatigue, orthopnea, paroxysmal nocturnal dyspnea, and angina (due to reduced coronary perfusion pressure during diastole paired with high oxygen demand from hypertrophied myocardium). Physical examination in chronic AR reveals striking hyperdynamic peripheral vascular signs driven by an abnormally wide pulse pressure (a high systolic pressure paired with an extremely low diastolic pressure). Classic clinical signs include Corrigan's pulse (water-hammer pulse), de Musset's sign (head bobbing with each heartbeat), Quincke's pulse (capillary pulsations in the nail beds), and Duroziez's sign (a double femoral murmur). A high-pitched, blowing decrescendo diastolic murmur is best heard at the left sternal border.
Diagnostic Evaluation Protocols and Advanced Cardiac Imaging
Establishing an accurate diagnosis and determining the timing of intervention in aortic regurgitation relies on multimodal cardiovascular imaging. Transthoracic Echocardiography (TTE) serves as the primary diagnostic modality, assessing valve morphology, quantifying regurgitation severity, and evaluating left ventricular dimensions and systolic function. Quantitative Doppler parameters—such as effective regurgitant orifice area (EROA), regurgitant volume, regurgitant fraction, and vena contracta width—categorize regurgitation as mild, moderate, or severe. TTE also tracks left ventricular end-diastolic diameter (LVEDD) and end-systolic diameter (LVESD), which serve as critical triggers for surgical timing. Transesophageal Echocardiography (TEE) provides superior anatomical visualization when evaluating aortic root pathology or infective endocarditis. Cardiac Magnetic Resonance (CMR) imaging is the gold-standard method for precise quantificationof regurgitant volume and left ventricular volumes, particularly when echocardiographic windows are suboptimal. Electrocardiography (ECG) typically shows left ventricular hypertrophy with strain patterns, while chest radiographs demonstrate cardiomegaly and aortic root dilation.
Therapeutic Management and Surgical Intervention Strategies
Medical therapy plays a limited role in definitive treatment of severe aortic regurgitation, serving primarily as a bridge to surgery or as management for comorbid hypertension. Vasodilators such as dihydropyridine calcium channel blockers or angiotensin-converting enzyme (ACE) inhibitors reduce systemic vascular resistance and afterload, marginally decreasing regurgitant volume in symptomatic patients or those with severe hypertension. The definitive treatment for severe aortic regurgitation is surgical intervention—either Aortic Valve Replacement (AVR) with a mechanical or bioprosthetic prosthesis, or aortic valve repair/aortic root reconstruction (such as the Bentall or David procedure) when root aneurysm is the primary etiology. Clinical guidelines recommend prompt surgical intervention for all symptomatic patients with severe AR, regardless of ejection fraction. In asymptomatic patients, surgery is indicated if objective evidence of left ventricular dysfunction or dilation emerges—specifically a left ventricular ejection fraction (LVEF) falling to or below fifty percent, or an LV end-systolic diameter exceeding fifty millimeters (or indexed to body surface area). Timely surgical correction before irreversible myocardial fibrosis occurs normalizes ventricular dimensions, prevents heart failure, and restores long-term survival.
Conclusion
Aortic Regurgitation is a significant valvular disease characterized by diastolic backward leakage through an incompetent aortic valve, driving chronic left ventricular volume and pressure overload. Understanding how eccentric hypertrophy compensates for massive regurgitant volumes—and how chronic wall stress eventually induces microvascular ischemia, cell death, and contractile failure—clarifies the transition from asymptomatic latency to overt heart failure. Utilizing transthoracic echocardiography, cardiac MRI, and Doppler quantification enables clinical teams to track left ventricular dimensions and detect early systolic dysfunction. Through timely surgical aortic valve replacement or repair prior to irreversible left ventricular decompensation, healthcare professionals can effectively eliminate regurgitation, reverse structural remodeling, and ensure long-term cardiovascular health for affected patients.