Understanding Common Disorders of the Parathyroid Glands
Human physiological stability depends profoundly upon an intricate endocrine network that regulates mineral concentrations across every organ system, with the parathyroid glands governing systemic calcium and phosphorus balance. Typically comprising four diminutive, disc-shaped structures nestled behind the thyroid gland, these tissues synthesize and secrete parathyroid hormone, the principal humoral agent controlling extracellular calcium ions. Under optimal physiological conditions, parathyroid hormone modulates skeletal resorption, renal tubular reabsorption, and intestinal mineral absorption via active vitamin D metabolites, maintaining serum calcium within a remarkably narrow therapeutic window. This precise hormonal feedback loop ensures normal neuromuscular excitability, cardiac muscle contraction, blood clotting, and skeletal density. However, when benign neoplasms, autoimmune destruction, or iatrogenic trauma compromise this endocrine axis, patients develop complex pathological states known collectively as parathyroid disorders.
Primary Hyperparathyroidism: Mechanisms of Autonomous Hypersecretion
Among endocrine abnormalities involving calcium metabolism, primary hyperparathyroidism stands out as a prevalent condition characterized by unregulated, excessive parathyroid hormone production originating from one or more hyperactive glands. In the vast majority of clinical presentations, this oversecretion stems from a benign monoclonal neoplasm termed a parathyroid adenoma, whereas diffuse four-gland hyperplasia or rare carcinomas account for remaining cases. Because parathyroid hormone continually mobilizes calcium from bone and enhances renal retention, chronic excess provokes persistent hypercalcemia. This biochemical disruption accelerates skeletal demineralization and stimulates renal synthesis of calcitriol, boosting intestinal mineral uptake. Consequently, primary hyperparathyroidism induces widespread systemic alterations that impact renal architecture, skeletal integrity, and vascular compliance.
Clinical Manifestations and Multisystem Consequences of Hypercalcemia
The clinical presentation of primary hyperparathyroidism has transitioned from classic overt disease featuring severe skeletal deformities to subtle manifestations frequently uncovered during routine blood evaluations. Nevertheless, when classic features emerge, clinicians often reference historical mnemonics encompassing painful bones, renal stones, abdominal groans, and psychic moans. Skeletal complications manifest as subperiosteal bone resorption, osteitis fibrosa cystica, and a heightened vulnerability to fragility fractures. Renal impacts involve recurrent nephrolithiasis, nephrocalcinosis, and polyuria driven by calcium-mediated tubular dysfunction. Gastrointestinal features include obstipation, nausea, peptic ulcer disease, and acute pancreatitis, while neuropsychiatric disruptions involve severe chronic fatigue, depressive symptoms, cognitive blunting, and generalized neuromuscular weakness.
Secondary and Tertiary Hyperparathyroidism in Chronic Renal Disease
Beyond primary glandular neoplasms, parathyroid hormone oversecretion frequently develops as an adaptive response to systemic illness, predominantly chronic renal insufficiency. In secondary hyperparathyroidism, failing nephrons lose their capacity to eliminate phosphorus and hydroxylate vitamin D, culminating in persistent hypocalcemia and hyperphosphatemia. This enduring biochemical stimulus drives all four parathyroid glands to undergo compensatory hypertrophy and amplify hormone synthesis to defend serum calcium levels. Over extended periods of chronic stimulation, these hyperplastic tissues can acquire autonomous cellular mutations, a pathological phase designated as tertiary hyperparathyroidism. In this refractory state, severe hypercalcemia persists despite adequate management of the underlying kidney disease or following renal transplantation, frequently demanding definitive surgical intervention.
Hypoparathyroidism: Endocrine Deficiency and Calcium Depletion
Conversely, when parathyroid hormone synthesis is suppressed or absent, individuals develop hypoparathyroidism, a rare endocrine deficiency marked by profound hypocalcemia and concurrent hyperphosphatemia. The leading etiology of this condition is iatrogenic trauma or inadvertent surgical excision of the parathyroid glands during complex cervical procedures, such as total thyroidectomies or radical neck dissections. Less common origins include autoimmune destruction, genetic developmental syndromes, and heavy metal infiltration. Deprived of parathyroid hormone, renal tubular calcium reabsorption plummets, active vitamin D production halts, and bone mineral mobilization ceases, causing circulating calcium concentrations to drop precipitously and destabilizing cellular membrane potentials.
Neuromuscular Irritability and Clinical Signs of Hypocalcemia
The hallmark physiological consequence of hypoparathyroidism is heightened neuromuscular excitability, spanning mild sensory anomalies to severe tetany. Affected individuals frequently report painful skeletal muscle cramps, carpopedal spasms, paresthesias around the oral cavity, and distal extremity numbness. During physical examinations, clinicians elicit latent tetany via classic diagnostic maneuvers: Chvostek's sign, where percussing the facial nerve anterior to the external auditory meatus provokes ipsilateral facial twitching, and Trousseau's sign, where inflating a sphygmomanometer cuff above systolic pressure induces characteristic carpal spasm. Severe acute hypocalcemia constitutes an urgent medical crisis, potentially triggering laryngospasm, generalized tonic-clonic seizures, cardiac arrhythmias, and significant prolongation of the QT interval on electrocardiographic readings.
Advanced Diagnostic Imaging and Laboratory Assessments
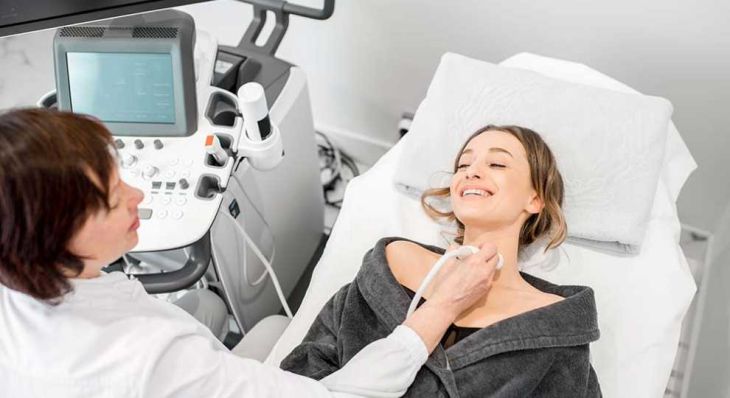
Establishing an accurate diagnosis for parathyroid abnormalities mandates a rigorous synthesis of biochemical assays and sophisticated localization imaging. Initial diagnostic confirmation relies on comprehensive laboratory panels evaluating serum calcium, intact parathyroid hormone, phosphorus, magnesium, 25-hydroxyvitamin D, and renal parameters like serum creatinine. In primary hyperparathyroidism, elevated or inappropriately normal parathyroid hormone paired with hypercalcemia confirms the diagnosis. Once biochemical parameters are established, preoperative localization studies assist surgical planning. Clinicians utilize high-resolution cervical ultrasonography, technetium-99m sestamibi scintigraphy, and four-dimensional computed tomography to pinpoint hyperfunctioning adenomas within the neck or superior mediastinum.
Therapeutic Strategies, Surgical Interventions, and Medical Management
Management protocols for parathyroid pathologies vary based on the underlying physiological mechanism, differentiating between hormone excess and hormonal deficiency. For primary hyperparathyroidism, definitive therapy for symptomatic or qualifying asymptomatic individuals involves parathyroidectomy, the surgical excision of the hyperactive tissue. Minimally invasive approaches, guided by preoperative imaging, allow surgeons to correct the disorder through small incisions with minimal postoperative morbidity. Conversely, medical management of hypoparathyroidism centers on lifelong oral calcium supplementation and active vitamin D analogs, such as calcitriol, supplemented by emerging recombinant parathyroid hormone therapies. For secondary and tertiary hyperparathyroidism, care focuses on dietary phosphorus restriction, oral phosphate binders, calcimimetic agents to suppress hormone release, and targeted surgical subtotal resection.
Conclusion
Parathyroid disorders encompass a diverse spectrum of hypersecretory and hyposecretory endocrine conditions that disturb mineral homeostasis throughout the body. By analyzing how primary hyperparathyroidism drives hypercalcemia and bone loss, recognizing the neuromuscular dangers of hypocalcemia, and utilizing advanced sestamibi imaging alongside intact hormone assays, clinicians can accurately diagnose these complex conditions. Through precise biochemical evaluation, targeted pharmacological agents, and advanced surgical techniques, medical professionals successfully restore mineral equilibrium, alleviate debilitating symptoms, and protect long-term systemic health.